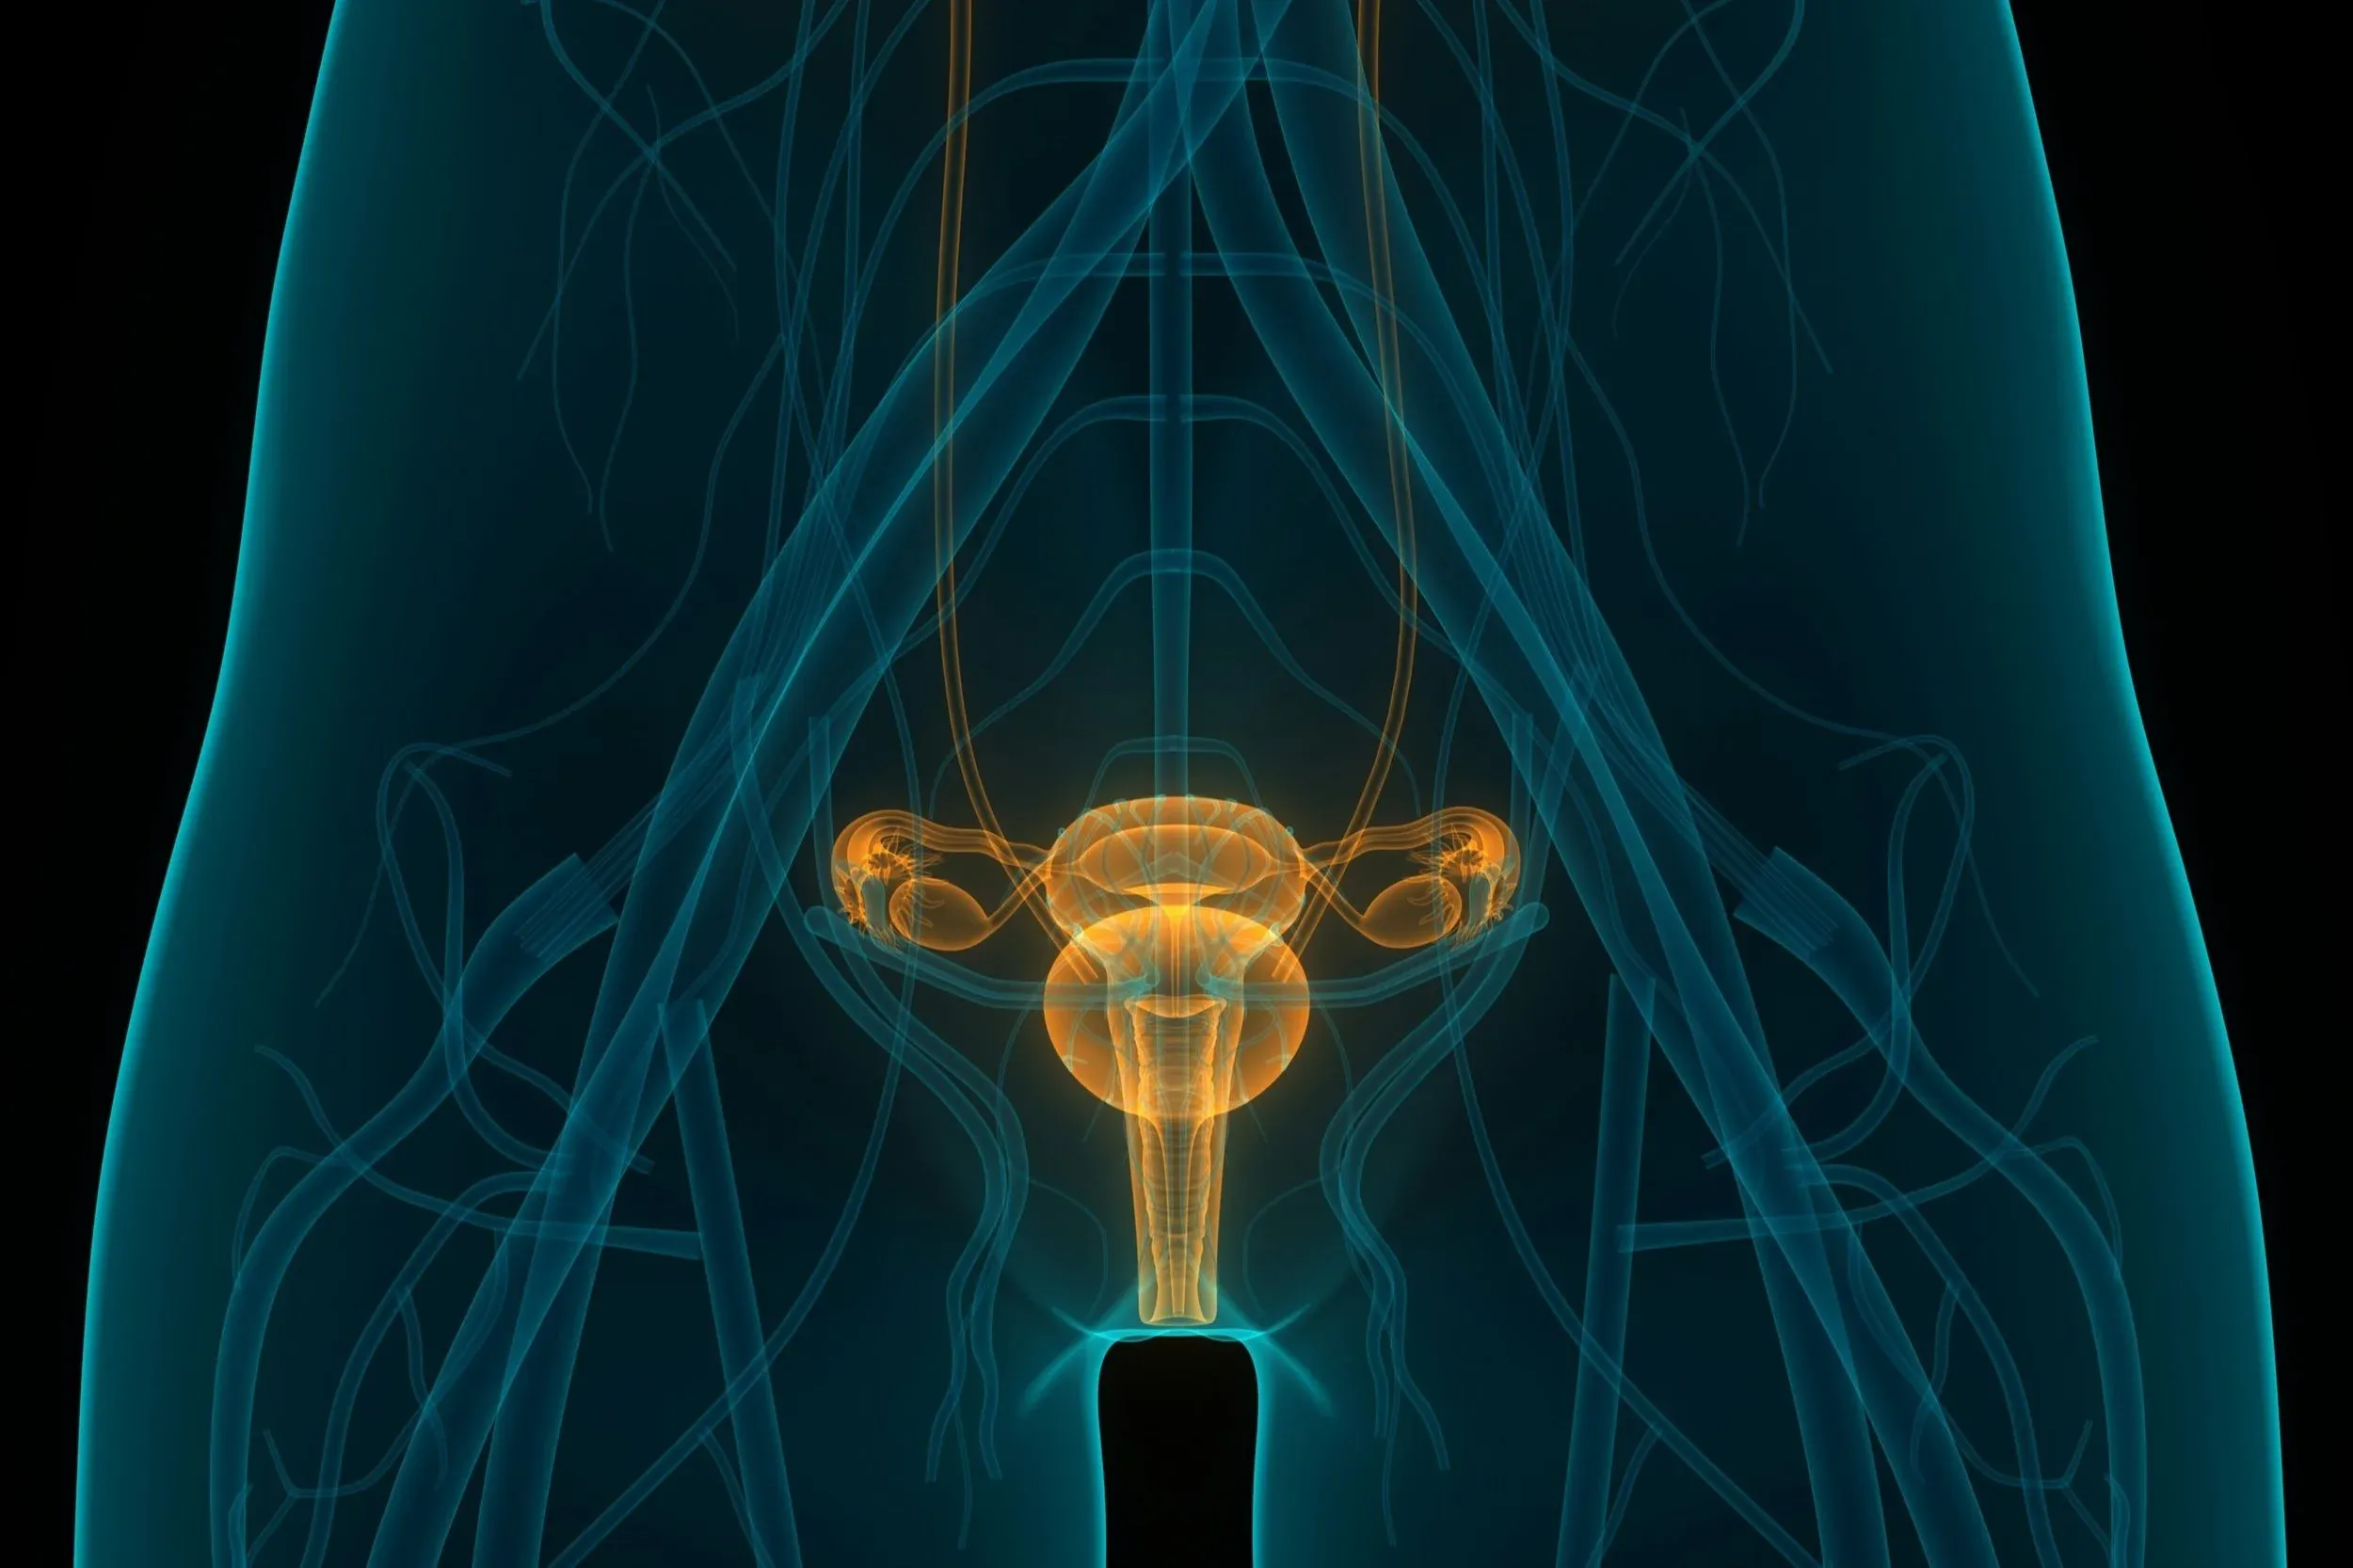
Urinary incontinence is common and undertreated.
It is estimated that up to 50% of women will have some urinary incontinence.
The General Longitudinal Overactive Bladder Evaluation – Urinary Incontinence (UI) (GLOBE-UI) is a population-based study on the natural history of UI in women aged over 40 years. Prevalence of UI was estimated by using the bladder health survey (BHS). Out of 7000 women- 47% responded and of them 41% suffered from urinary incontinence (1366). Only 25% of women with urinary incontinence seek help (339).
Women may be reluctant to seek assistance due to embarrassment, lack of knowledge about treatment options and fear of surgery.
Impact on health
- Quality of life– Urinary incontinence is associated with depression and anxiety, work impairment and social isolation
- Sexual dysfunction– Incontinence during sexual activity (coital incontinence), which may affect up to one-third of all incontinent individuals, and fear of incontinence during sexual activity both contribute to incontinence-related sexual dysfunction
- Morbidity– skin irritation and perineal infection can occur with chronic cases of urinary incontinence. In older women, UI is associated with an increased risk of falls.
Risk factors
- Age – Both the prevalence and severity of urinary incontinence increase with age. UI affects 3% of adult women under age 35, and 38% of women over age 60.
- Obesity– Obesity is a strong risk factor for incontinence. Obese women have a nearly threefold increased odds of urinary incontinence compared with non-obese women. Weight reduction is associated with improvement and resolution of urinary incontinence, particularly stress urinary incontinence (SUI)
- Parity– Increasing parity (how many babies a woman has given birth to) is a risk factor for urinary incontinence and pelvic organ prolapse
- Mode of birth/obstetric delivery– Compared with women who have had a caesarean section, women who have had a vaginal delivery are at higher risk for stress urinary incontinence. However, caesarean delivery does not completely protect women from urinary incontinence
- Family history– The risk of urinary incontinence, particularly urge incontinence, may be higher in patients with a family history
- Others
- Smoking increases a woman’s risk of UI.
- Stress urinary incontinence has been associated with participation in high-impact activities.
- Other risk factors for urge incontinence include recurrent urinary tract infections (UTIs) and bladder symptoms in childhood, including childhood nocturnal enuresis
Classification
Stress incontinence — Individuals with stress incontinence have involuntary leakage of urine that occurs with increases in intra-abdominal pressure (e.g., with exertion, sneezing, coughing, laughing) in the absence of a bladder contraction.
Urge incontinence — Women with urge incontinence experience the urge to void immediately preceding or accompanied by involuntary leakage of urine. The amount of leakage ranges from a few drops to completely soaked undergarments. Urge incontinence is more common in older women.
Overflow incontinence — Overflow incontinence typically presents with continuous urinary leakage or dribbling in the setting of incomplete bladder emptying.
Mixed incontinence – Contributing factors
- In post-menopausal women, low estrogen levels contribute to urinary incontinence
- Rare conditions, such as fistula and diverticula can occur as the result of vaginal birth trauma
- Neurological conditions, such as stroke, Parkinson’s disease or diabetic neuropathy can cause bladder muscle damage or loss of control.
- Bladder cancer and it’s treatments can cause UI
Evaluation
Usually, diagnosis can be made based on history taking and examination.
- Some medications can contribute to urinary incontinence
- Alcohol and caffeine intake have been associated with lower urinary tract symptoms
- Caffeine intake exacerbates urinary incontinence due to its stimulant and diuretic effects
- Impact on quality of life —The impact of the patient’s incontinence on her quality of life can be assessed informally by asking a few targeted questions or by using a validated questionnaire
- Urine test- to check for blood/ abnormal cells and/or infection
- Initial evaluation does not require invasive testing, such as urodynamic studies
Women’s Health Melbourne is a comprehensive CREI lead fertility and women’s health practice, offering the full spectrum of menopause and gynaecology services, together with natural and medical specialist fertility treatment modalities.